Profile of Respiratory Viral Infections in Sickle Cell Anemia: H1N1 Co-Infection not a Significant Issue?
Alkindi S1,2*, Yahyai T1, Raniga S3, Boulassel MR2,4 and Pathare AV1
1Department of Haematology, Sultan Qaboos University Hospital
2College of Medicine & Health Sciences, Muscat, Oman
3Department of Radiology & Molecular Imaging, Sultan Qaboos University Hospital
4Department of Allied Health Sciences
*Address for Correspondence: Salam Alkindi, Department of Haematology, College of Medicine & Health Sciences, Sultan Qaboos University, P. O. Box 35, Muscat 123, Sultanate of Oman, Tel: +968-241-411-82; Fax: +968-241-448-87; E-mail: [email protected]
Submitted: 28 July 2019; Approved: 01 August 2019; Published: 03 August 2019
Citation this article: Alkindi S, Yahyai T, Raniga S, Boulassel MR, Pathare AV. Profile of Respiratory Viral Infections in Sickle Cell Anemia: H1N1 Co-Infection not a Significant Issue. Int J Virol Infect Dis. 2019;4(1): 001-005.
Copyright: © 2019 Alkindi S, et al. This is an open access article distributed under the Creative Commons Attribution License, which permits unrestricted use, distribution, and reproduction in any medium, provided the original work is properly cited
Keywords: Sickle cell anemia; Viruses; Respiratory; H1N1
Download Fulltext PDF
Background: Patients with Sickle Cell Anemia (SCA) are immunocompromised and at an increased risk of developing infections. A retrospective cross-sectional study was conducted in SCA patients with respiratory viral infections. After approval of the study from the local medical research and ethics committee, demographic data, clinical, radiological and laboratory parameters were collected and analysed.
Results: In eighty-four SCA patients with one hundred and nine admission episodes for Vasooclusive Crisis (VOC), molecular diagnostic techniques confirmed one twenty-five respiratory viral infections. Rhinovirus was the most prevalent infection (35.8%), whereas, H1N1 virus infection was seen only in 10.1%. Laboratory investigations revealed a significant fall in the mean hemoglobin, mean WBC and platelet counts from baseline, whereas, there was a significant rise in the mean lymphocyte and retic count, serum LDH and CRP levels during infective episodes (p < 0.05, Wilcoxon signed rank test). 32.1% of the VOC episodes progressed to Acute Chest Syndrome (ACS), but in the H1N1 cohort, ACS was seen in only two episodes (18.2%).
Conclusions: Rhinovirus was the commonest respiratory virus infections in SCA patients, whereas, parainfluenza 3 was associated with a significant adverse outcome. H1N1 was associated with a mild course. ACS was seen in approximately one third of this group of patients.
Introduction
Sultanate of Oman is located on the southeastern coast of the Arabian Peninsula, with a largely tribal society. Haemoglobinopathies are very common (due to high consanguineous marriage), with an estimate of more than two per 1,000 live births are affected [1-3]. The prevalence of serious haemoglobinopathies in Oman is about 10% with the most significant being sickle cell anemia, and β-Thalassemia Major (TM) [3].
In SCA, there is a point mutation producing Hb-S instead of Hb-A by changing glutamic amino acid into valine leading to abnormal β chain production [4,5]. About 40% of hemoglobin in the sickle cell trait is Hb-S, but in homozygosity, it can reach up to 80-95% [6]. The resulting Hb-S can polymerize easily under the low oxygen levels in post-capillary veins, causing sickling and vaso-occlusive events leading to tissue inflammation, destruction and end organ damage [7]. The disease is characterized by the triad of recurrent painful episodes (crises) that occurs suddenly in any part of the body, especially in the bones and joints of limbs, abdomen and chest; hemolytic anemia, and a predisposition to repeated infections [7,8]. The clinical manifestations of SCA vary from patient to patient depending on the severity of the disease, and this is influenced by many factors, including environmental factors, but also in particular by the level of fetal hemoglobin (Hb-F) in postnatal life [9].
SCA patients are at an increased risk of infections, and so they are considered as inherently immunocompromised, due to splenic dysfunction, altered complement regulation, low oxygen tension, medications, and recurrent admissions to hospital with exposure to nosocomial pathogens [6,8]. The prevalence of infections has apparently increased and may be related to the improved diagnostics in recent times.
Among these infections, respiratory viral infections are very common, and can affect both upper and lower respiratory tract. The comprehensive study of SCA in United States demonstrated that viruses contributed to 6.7% of cases progressing to ACS7. Previous studies showed that three new respiratory viruses had emerged, namely, SARS (a novel Corona virus) in 2003, influenza A H5N1 (Avian flu) in 2004, and the pandemic caused by the new reassortant influenza A (H1N1) in April 2009, which was first identified in Mexico and California with subsequent spread worldwide [10]. In Oman, 2681 persons have been reported to have been infected with influenza A (H1N1) virus, of which 24 patients died, with these deaths occurring in the very young or elderly or those with underlying disease [11].
Respiratory infections are a risk factor for triggering ACS in SCA patients and often lead to several complications. Bundy DG et al. [12] showed that influenza-associated hospitalization and complications in pediatric SCA patients was 56 times higher than in non-SCA patients. Measures to control these infections will immensely benefit these patients who are highly susceptible to infections; in particular with increasing prevalence of viral infections after the pandemic of H1N1. The Center of Disease Control and Prevention also recommends regular vaccination for the prevention and control of seasonal influenza [13], and this is essential in SCA patients with their inherent immunocompromised state.
However, there has been limited data in published literature studying the effect of respiratory viral infections and in particular H1N1 infections on SCA patients. Inusa B et al. [14] reporting from UK, estimated H1N1 in 50 % of the SCA patients presenting to the hospital with 25% developing ACS. Further, George A et al [15] reported that in 48 cases of H1N1 influenza, 21% progressed to ACS. Strouse J et al. [16] reported that in children and young adults with SCA, they identified 29 cases of confirmed H1N1 infection, with 34% developing ACS and 17% required intensive care including mechanical ventilation in 10%.
Aims & Objectives
In this study, we retrospectively analyzed hundred and nine admission episodes in eighty-four patients with SCA who were confirmed molecularly with laboratory diagnostics to have respiratory viral infections, with the aim to establish the clinical, laboratory and radiological manifestations and assess its impact on the disease morbidity and mortality, with special emphasis on H1N1.
Materials & Methods
A retrospective Electronic Medical Records (EMR) review was carried out after approval by the local hospital medical research and ethics committee. A list of four hundred and twenty-eight patients with SCA who were tested for viral infections were obtained from the EMR, but only eighty-four patients with a total of hundred and nine admission episodes met all the inclusion criteria namely: age of fifteen years old or above, confirmation of SCA by high-performance liquid chromatography and/or DNA studies and confirmation of respiratory viral infection by molecular studies (Viral RNA/DNA PCR). All of these events occurred in the period between June 2013 and July 2018. Information on demography, past history, clinical and laboratory findings, chest radiographs, complications, co-infections, interventions and drugs given related to the episodes of respiratory viral infections in these patients were retrieved for analysis.
Statistical Analysis
The statistical package for social science (IBM SPSS, USA ver.23) was used to analyze the collected data. Continuous variables were expressed as mean and standard deviation in case they were normally distributed, and median and Inter Quartile Range (IQR) for data not following normal distribution. Nonparametric tests like chi-square was used to determine the statistical significance and the unpaired t-test Wilcoxon signed ranks test were used to compare means of continuous variables between groups. A p value < 0.05 was consider significant.
Results
In this study cohort, the males and females were equally represented (n = 42 each) with a mean age + SD of 27 ± 7 and range between 15 to 57 years. Admission episodes were also almost equally divided with 55 and 54 episodes in the male and female patients respectively. Clinical details and confounding factors showed that 89% patients were on penicillin prophylaxis whereas, 61.5% were on hydroxyurea therapy. 38.5% showed asplenia on abdominal ultrasound, either owing to surgical splenectomy or autosplenectomy, whereas, 58.7% had a previous history of ACS.
Generally, the clinical presentations were similar in all the types of respiratory viral infections. The most frequent signs and symptoms seen in these SCA patients were pain (87.2%), fever (55.1%) with a mean duration of 3 days; and cough (55.1%), ranging from dry to productive. Other frequent symptoms were throat congestion (23.8%), chest pain (22.1%), crepitation (22.9%), reduced air-entry (16.5%), headache (11.9%) and rhinorrhea (14.7%) as shown in figure 1. Comparatively, H1N1 patients had a higher incidence of cough (72.7% v/s 53.1%), rhinorrhea (36.4% v/s 14.7%), reduced air entry (18.2% v/s 16.3%); crepitation (27.3% v/s 22.9%) than other non-H1N1 respiratory viral infected SCA patients in this cohort.
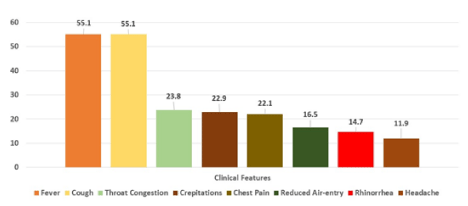
Table 1a shows the details of haematological parameters by a comparison between the baseline and the data at the time of infection. It was observed that the median hemoglobin (IQR) (g/ dl) at baseline 11.45 (1.5) was significantly higher than the median hemoglobin [nadir] during the infection at 7.25(1.2) (p < 0.001). Mean WBC (± SD) (X109/ L) at baseline was significantly decreased to 6.8 (2.5) from its baseline value of 8.9 (3.4) during infection [p < 0.002, Wilcoxon signed ranks test]. Median (IQR) reticulocyte count (X109/ L) at baseline of 214.5 (230.9) was significantly higher than during infection 169.5 (84) [p < 0.005, Wilcoxon signed ranks test]. Mean platelets (± SD) (X109/ L) at baseline was significantly decreased to 285.2 (207.9) from its baseline value of 350.6 (252.4) during the infection [p < 0.001, Wilcoxon signed ranks test]. Median lymphocytes count (IQR) at baseline 2.7(0.9) (X109/ L) was significantly lower than the median lymphocytes [Max] during the infection at 3.7(1.8) [p < 0.001, Wilcoxon signed ranks test].
Table 1b summarizes the biochemical parameters. We observed that the median C-Reactive Protein (CRP) mg/L (IQR) at admission was significantly lower 18.5(41) than the median CRP [Max] during the infection 143.5 (147) [p <0.001, Wilcoxon signed ranks test]. Median lactate dehydrogenase (LDH) u/ L (IQR) has significantly increased to 710.5 (991) from its baseline value of 350 (162) during the infection [p < 0.001, Wilcoxon signed ranks test].
Abnormal chest radiological findings were present in 25%, with segmental (10%) or multi-segmental atelectasis (8%), and ARDS (7%). Pleural effusions were seen in 22% with 19% going through a mild course, but 3% had a moderate effusion.
Figure 2 shows the interventions and complications in these patients with respiratory virus infection. Interventions included blood transfusions (44.9%), non-invasive ventilation (12.8%), need for central venous catheter (7.3%) and urinary catheter (3.7%). 32.1% of these episodes were complicated by ACS and was associated with one death. Overall, two patients died in this cohort and both the patients were infected with Parainfleunza 3 virus. First patient had a co-associated Salmonella and developed sepsis and died. The other patient had a co-associated ACS and developed seizures with neurological symptoms, bradycardia that was managed by implantable cardiac defibrillator, but also died.
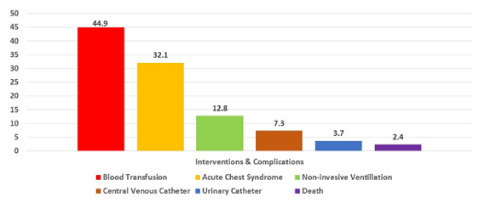
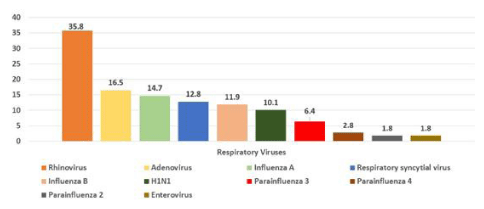
Figure 3 shows the spectrum of respiratory viruses (n = 125) observed in this study with 10.1% showing H1N1. The most prevalent non-H1N1 respiratory virus infection was with rhinovirus (35.8%), followed by adenovirus (16.5%), influenza A (14.7%), respiratory syncytial virus [RSV] (12.8%), influenza B (11.9%), parainfluenza 3 (6.4%), parainfluenza 4 (2.8%), enterovirus (1.8%), parainfluenza 2 (1.8%). In all cases, the diagnosis the specific viral infection was made by molecular studies with reverse-transcriptase polymerase chain reaction to identify the relevant viral RNA or DNA.
In 84.4%, infection was due to a single virus, whereas, in the remaining 15.6%, multiple viral organisms were found. Importantly, less than a third of these patients with multiple viruses were associated with ACS (23.5%). But significantly, all H1N1 cases were co-associated with influenza A virus (100%). Additionally, bacterial co-infection in five instances with six different microorganisms, and two instances of a co-infection with both a viral and a fungal microorganism were also observed.
Table 2 shows the comparison of the clinical and radiological features, interventions and complications in patients with and without H1N1 infections. There were no statistically significant differences seen.
Discussion
The purpose of this study was to investigate the impact of respiratory viral infections in the patients with SCA attending our hospital. In general, our data showed that these patients presented with upper respiratory tract infection symptoms with varying degree of severity but there were no significant differences in clinical presentations between the different types of the respiratory viruses. Relatively speaking, more severe symptoms were seen in those patients infected with adenovirus and Parainfluenza 3 virus. Further, these findings were consistent with the previous reports about the general impact of respiratory viruses in patients with SCA [7]. ACS was seen in only 32.1% with low mortality, although two-thirds of this cohort were on hydroxyurea and had a previous history of ACS as well as in addition a third also had splenectomy or asplenia.
The mean age in H1N1 patients was higher than the non-H1N1 patient cohort (28.8 vs. 26.5 years). Although, there was no differences in the common symptoms of infection between the two groups, in H1N1 patients, fever and rhinorrhea were relatively predominant, whereas, in the non-H1N1 patient’s painful episodes, blood transfusions, and ACS were more prominent, but these differences were not statistically significant (Table 2). The clinical course in the H1N1 patients, was mild with only two patients needing morphine and one patient needed chest physiotherapy and incentive spirometry.
Although the comprehensive sickle cell study from United States demonstrated that viruses contributed to only 6.7% of cases progressing to ACS [7], influenza-associated hospitalization in SCA is reported to be 56 times higher [12]. George et al. [15] had reported that the impact of H1N1 influenza pandemic on SCA patients was mild with 21% progressing to ACS. A prior study by Strouse J et al. [16] had also reported significant morbidity. In their study on H1N1 influenza patients, 34% progressed to ACS, requiring invasive care in 17%, while 10% needed mechanical ventilation. In our H1N1 cohort (n = 11), two patients progressed to ACS (18.2%), and although none needed intensive care, one (9%) required non-invasive ventilation but none died. It is believed that the overall improvement in the SCA management may be responsible for these improved outcomes. Further, the role of early institution of oseltamivir also needs to be emphasized as all our patients received it early when the diagnosis was suspected.
Expectedly, the laboratory parameters worsened after infection. Similar to previous studies [7,17], we found that there was a decline in oxygen saturation and hemoglobin levels; with development of thrombocytopenia, leukopenia and lymphocytosis (p < 0.05, Wilcoxon signed rank test). Also, the significant increase in CRP and serum LDH indicated that there was intense ongoing inflammation with organ ischemia and tissue infarction. These findings were similar in all respiratory viruses and suggest that the serial monitoring is necessary in addition to proactive expectant supportive management.
Monitoring by chest imaging was done in all these patients as they were most likely to trigger the development of ACS. We relied on the new changes occurring in the infection episodes with regards to chest infiltrates because the radiographs may be normal at the start of the infection. Our findings showed that the most severe radiological changes were seen with adenoviruses. Cha MJ et al. [18], in a study from Korea, reported that adenovirus pneumonia progressed to ARDS in 63%, with 50% mortality. Adenovirus respiratory infections are usually associated with bilateral patchy parenchymal or ground-glass opacities on chest radiographs [19]. Magdy et al. [20], reported that the predominant radiological pattern seen in H1N1 infection was bilateral ground glass opacities and alveolar consolidation. However, the radiological changes seen in H1N1 cases in this study were mild and unilateral. Again, we feel that the improved management of SCA in general and the specifically the early institution of drug Oseltamivir may have played an important role here. Nevertheless, further larger studies will be needed to explain these differences.
It has been found that viral infections can promote bacterial adherence and immune-mediated interactions [21]. Our study demonstrated that the co-infections were mostly detected with rhinovirus followed by adenovirus showing the highest prevalence of co-association with bacterial organisms. However, our study cohort showed a lower prevalence of bacterial co-infections (6%) than a previous study by Seo et al. [22] reporting the prevalence of 26.5%. However, despite the low prevalence, there was a prolonged length of hospital stay and a more severe infection course in these patients with bacterial co-infection. Furthermore, a higher mortality was also seen.
Summary and Conclusions
In conclusion to our knowledge, this is the first study from Oman that reports the impact of respiratory viruses on clinical, radiological and laboratory manifestations in SCA patients. Our findings indicated that SCA patients displayed a mild course of H1N1 infection and the most prevalent respiratory virus in this cohort was rhinovirus. Fever and cough were the most frequent presenting symptoms, leading to significant anemia, reticulocytopenia, leucopenia and thrombocytopenia. Also, LDH and CRP were significantly elevated. Nearly one third had ACS and almost half required blood transfusions. Further, the most severe course was seen in SCA patients infected with adenovirus or parainfluenza 3 virus, with mortality associated with the latter. However, studies on a larger number of patients with respiratory infections are necessary to further evaluate other factors that may predispose patients with SCA to develop these viral infections.
Acknowledgement
We wish to thank the hospital administration for the use of hospital material in this study.
Disclosure of Conflict of Interests
The authors report no conflicts of interest. The authors alone are responsible for the content and writing of this article. This research did not receive any specific grant from funding agencies in the public, commercial, or not-for-profit sectors.
Authorship
All authors have made substantial contributions and have seen the final version. (1) SK, TY, SR, MRB were fully involved in the conception and design of the study, or acquisition of data, or analysis and interpretation of data, (2) SK and AVP were instrumental in the drafting the article and critical appraisal before submission.
- Rajab A, Patton MA. A study of consanguinity in the Sultanate of Oman. Ann Hum Biol. 2000; 27: 321-326. https://bit.ly/2yuOdS2
- Al Riyami AA, Suleiman AJ, Afifi M, Al-Lamki ZM, Daar S. A community-based study of common hereditary blood disorders in Oman. East Mediterr Health J. 2001; 7: 1004-1011. https://bit.ly/2LTgJpb
- Alkindi S, Al Zadjali S, Al Madhani A, Daar S, Al Haddabi H, Al Abri Q, et al. Hemoglobinopathy Burden through neonatal screening in Omani neonates. Hemoglobin. 2010; 34: 135-144. https://bit.ly/3315Dni
- Hassan SM, Vossen RH, Chessa R, den Dunnen JT, Bakker E, Giordano PC, et al. Molecular diagnostics of the HBB gene in an Omani cohort using bench-top DNA Ion Torrent PGM technology. Blood Cells Mol Dis. 2014; 53: 133-137. https://bit.ly/2GG3949
- Bunn HF. Pathogenesis and treatment of sickle cell disease. N Engl J Med. 1997; 337; 762-769. https://bit.ly/333a5Sx
- Porth C. Essentials of pathophysiology. Philadelphia: Wolters Kluwer/Lippincott; Williams & Wilkins. 2011. https://bit.ly/2YluovU
- Vichinsky EP, Neumayr LD, Earles AN, Williams R, Lennette ET, Dean D, et al. Causes and outcomes of the acute chest syndrome in sickle cell disease. National Acute Chest Syndrome Study Group. N Eng J Med. 2000; 342: 1855-1865. https://bit.ly/3348LyL
- Alkindi S, Matwani S, Al-Maawali A, Al-Maskari B, Pathare A. Complications of PORT-A-CATH® in patients with sickle cell disease. J Infect Public Health. 2012; 5: 57-62. https://bit.ly/33ex0KS
- Hassan SM, Al Muslahi M, Al Riyami M, Bakker E, Harteveld CL, Giordano PC. Sickle cell anemia and α-thalassemia: a modulating factor in homozygous HbS/S patients in Oman. Eur J Med Genet. 2014; 57: 603-606. https://bit.ly/2Yl0TdB
- Writing Committee of the WHO Consultation on Clinical Aspects of Pandemic (H1N1) 2009 Influenza, Bautista E, Chotpitayasunondh T, Gao Z, Harper SA, Shaw M, Uyeki TM, et al. Clinical aspects of pandemic 2009 influenza A (H1N1) virus infection. N Engl J Med. 2010; 362: 1708-1719. https://bit.ly/2GDTjju
- Al-Mahrezi A, Samir N, Al-Zakwani I, Al-Muharmi Z, Balkhair A, Al-Shafaee M. Clinical characteristics of influenza A H1N1 versus other influenza-like illnesses amongst outpatients attending a university health center in Oman. Int J Infect Dis. 2012; 16: e504-507. https://bit.ly/2ZmI7Pz
- Bundy DG, Strouse JJ, Casella JF, Miller MR. Burden of influenza-related hospitalizations among children with sickle cell disease. Pediatrics. 2010; 125: 234-243. https://bit.ly/2LWV1Ar
- Recommendations of the Advisory Committee on Immunization Practices--United States, 2013-2014. MMWR Recomm Rep. 2013; 62: 1-43. https://bit.ly/2KiLPDx
- Inusa B, Zuckerman M, Gadong N, Afif M, Arnott S, Heath P, et al. Pandemic influenza A (H1N1) virus infections in children with sickle cell disease. Blood. 2010; 115: 2329-2330. https://bit.ly/2YAuevR
- George A, Benton J, Pratt J, Kim MO, Kalinyak KA, Kalfa TA, et al. The impact of the 2009 H1N1 influenza pandemic on pediatric patients with sickle cell disease. Pediatr Blood Cancer. 2011; 57: 648-653. https://bit.ly/2OwbD4d
- Strouse JJ, Reller ME, Bundy DG, Amoako M, Cancio M, Han RN, et al. Severe pandemic H1N1 and seasonal influenza in children and young adults with sickle cell disease. Blood. 2010; 116: 3431-3434. https://bit.ly/2GI4E1N
- Vichinsky EP, Styles LA, Colangelo LH, Wright EC, Castro O, Nickerson B. Acute chest syndrome in sickle cell disease: clinical presentation and course: cooperative study of sickle cell disease. Blood. 1997; 89: 1787-1792. https://bit.ly/2K9zFxF
- Min Jae Cha, Myung Jin Chung, Kyung Soo Lee, Tae Jung Kim, Tae Sung Kim, Semin Chong, et al. Clinical features and radiological findings of adenovirus pneumonia associated with progression to acute respiratory distress syndrome: a single center study in 19 adult patients. Korean J Radiol. 2016; 17: 940-949. https://bit.ly/2OBeI2Y
- Chong S, Lee KS, Kim TS, Chung MJ, Chung MP, Han J. Adenovirus pneumonia in adults: radiographic and high-resolution CT findings in five patients. AJR Am J Roentgenol. 2006; 186: 1288-1293. https://bit.ly/2KiW3DI
- Magdy A, Haytham SD, Yasser R. Radiological findings in patients with H1N1 influenza pneumonia, Egyptian Journal of Chest Diseases and Tuberculosis. 2016; 65: 135-142. https://bit.ly/2LUgTwp
- McCullers JA, McAuley JL, Browall S, Iverson AR, Boyd KL, Henriques Normark B. Influenza enhances susceptibility to natural acquisition of and disease due to Streptococcus pneumoniae in ferrets. J Infect Dis. 2010; 202: 1287-1295. https://bit.ly/2YjbRjU
- Seo YB, Song JY, Choi MJ, Kim IS, Yang TU, Hong KW, et al. Etiology and clinical outcomes of acute respiratory virus infection in hospitalized adults. Infect Chemother. 2014; 46: 67-76. https://bit.ly/2MvR9WJ
Sign up for Article Alerts